Tuesday, May 7, 2013

Worse than nothing: the single-minded focus on biological psychiatry
Two articles published this week describe NIMH’s recent (and long, long overdue) turn away from the APA’s “Bible,” the DSM: John Horgan’s “Psychiatry in Crisis! Mental Health Director Rejects Psychiatric 'Bible' and Replaces with… Nothing” on his Scientific American blog and Christopher Lane’s “The NIMH Withdraws Support for DSM-5: The latest development is a humiliating blow to the APA” on his blog at Psychology Today.
Horgan reports:
Now, in a move sure to rock psychiatry, psychology and other fields that address mental illness, the director of the National Institutes of Mental Health has announced that the federal agency–which provides grants for research on mental illness–will be “re-orienting its research away from DSM categories.”Lane also recognizes the importance of the change:
In a humiliating blow to the American Psychiatric Association, Thomas R. Insel, M.D., Director of the NIMH, made clear the agency would no longer fund research projects that rely exclusively on DSM criteria.Both writers also recognize, though, that, while this represents in some ways a needed step forward, characterizing it as a death blow to the status quo isn’t entirely correct. Horgan argues that Insel’s smoke and mirrors can’t hide the fact that NIMH has nothing with which to replace the unscientific DSM:
…The manual's authority won't end overnight, but, given the implications of the NIMH's decision, it also can't and won't stay as it has.
So the NIMH is replacing the DSM definitions of mental disorders, which virtually everyone agrees are profoundly flawed, with definitions that even he admits don’t exist yet! What more evidence do we need that modern psychiatry is in a profound state of crisis?He very reasonably argues that this futuristic rhetoric has real consequences for real people and needs to stop:
Since I became a science writer 30 years ago, I have heard countless claims about breakthroughs in our understanding and treatment of mental illness. And yet as the NIMH decision on the DSM indicates, the science of mental illness is still appallingly primitive. Instead of forming fancy new programs and initiatives and alliances, leaders in mental health should perhaps do some humble, honest soul searching before they decide how to proceed.Lane, similarly, notes that “the alternatives, at least those that the NIMH is presenting, may turn out to be equally problematic and unworkable.” Quoting the same assumptions underlying the NIMH project as I did in my previous post, he points out that “These assumptions spring from assertions and tautologies that have driven American psychiatry since at least the 1970s.” As he makes clear, it’s the “single-minded focus on biological psychiatry as the represented solution” that’s at the heart of the problem. NIMH’s “overwhelming focus is to remain on the brain as the alleged seat and cause of psychiatric suffering,” despite the demonstrated failure and scientific fruitlessness of that project. As these articles recognize, that approach, in practice, is a lot worse than nothing. In an upcoming post I’ll elaborate further on how holding to the genetic science fiction model is irrational and harmful.
Sunday, May 5, 2013
Spinning the failure of biopsychiatry
The brain-disease-drug crowd has been singing the same tired, misleading refrain for a while now. It’s in two parts.
The first consists of the seemingly courageous admission that what the psychiatric profession, pharmaceutical companies, and government agencies have been claiming is the established science behind the “brain disease,” “mental illness” conception of psychic distress…well, isn’t.* Turns out, it’s been bogus and hollow from the start. The scientific diagnoses have nothing behind them, and the so-called hypotheses at the heart of the model have now been discarded.
A few examples:
An NPR story by Alex Spiegel from last year:
And really, it is because of the popularity of Prozac that the low-serotonin story took hold, even though, Frazer argues, the scientific research has not borne that out.A recent piece in Nature by David Adam:
"I don't think there's any convincing body of data that anybody has ever found that depression is associated to a significant extent with a loss of serotonin," he says.
DSM-5, like the two preceding editions, will place disorders in discrete categories such as major-depressive disorder, bipolar disorder, schizophrenia and obsessive–compulsive disorder (OCD). These categories, which have guided psychiatry since the early 1980s, are based largely on decades-old theory and subjective symptoms.Another recent article by NIMH head Thomas Insel:
The problem is that biologists have been unable to find any genetic or neuroscientific evidence to support the breakdown of complex mental disorders into separate categories.
…Despite decades of work, the genetic, metabolic and cellular signatures of almost all mental syndromes remain largely a mystery.
The goal of this new manual, as with all previous editions, is to provide a common language for describing psychopathology. While DSM has been described as a “Bible” for the field, it is, at best, a dictionary, creating a set of labels and defining each. The strength of each of the editions of DSM has been “reliability” – each edition has ensured that clinicians use the same terms in the same ways.** The weakness is its lack of validity. Unlike our definitions of ischemic heart disease, lymphoma, or AIDS, the DSM diagnoses are based on a consensus about clusters of clinical symptoms, not any objective laboratory measure. In the rest of medicine, this would be equivalent to creating diagnostic systems based on the nature of chest pain or the quality of fever. Indeed, symptom-based diagnosis, once common in other areas of medicine, has been largely replaced in the past half century as we have understood that symptoms alone rarely indicate the best choice of treatment.Steven E. Hyman, last month***:
The scientific issues facing translational psychiatry—the application of basic discoveries in neuroscience, genetics, and psychology to understanding disease and to advancing therapeutics—are daunting. The molecular and cellular underpinnings of psychiatric disorders remain unknown; there is broad disillusionment with the animal models used for decades to predict therapeutic efficacy; psychiatric diagnoses seem arbitrary and lack objective tests; and there are no validated biomarkers with which to judge the success of clinical trials.A natural and reasonable response to the statements I’ve bolded would be to stop, step back, and consider the import of these acknowledgements. It’s being conceded that these biological disorders, as such, don’t exist. The premise for the alleged effectiveness of the drugs being prescribed to and sometimes forced upon people around the world - costing billions of dollars, causing harm, and diverting resources from potentially fruitful investigations and approaches - is invalid. The existing brain disease model is false.
In fact, reports of these facts are, regularly and repeatedly, treated as “explosive,” only to be greeted as explosive again months or years later. It would seem astounding that people haven’t been enraged and that this hasn’t much altered the status quo. But some of the explanation (in addition to the pharmaceutical companies’ huge propagandistic capacity) for the failure of these particular articles to cause widespread uproar can be found in the way they’re framed.
First, these stories tend to minimize and distort the admissions. Spiegel’s piece, for example, is titled “When It Comes To Depression, Serotonin Isn’t The Whole Story,” and contains this passage:
Coyle is less absolute in his dismissal of the evidence on serotonin. His take is that while low serotonin probably doesn't cause depression, some abnormality in the serotonin system clearly plays a role. But most researchers have moved on, he says, and are looking at more fundamental issues like identifying the genes that might put people at risk for developing depression.So in some cases the current brain-disease model isn’t really fully acknowledged to be false, as it would at first seem. To some extent, it’s presented as just a part of a larger story or a simplified, superficial, or reductionistic version of a complex explanation. This parallels the evasive response received by Leo and Lacasse when they tried to challenge deceptive direct-to-consumer advertising of antidepressants based on the monoamine “hypothesis”:
"What's being looked at are processes that are much more fundamental than just serotonin levels," he says. "We need to move beyond serotonin, and I think the field is."
Since 2002, the first author (JRL) has repeatedly contacted the FDA regarding these issues. The only substantive response was an E-mail received from a regulatory reviewer at the FDA: “Your concern regarding direct-to-consumer advertising raises an interesting issue regarding the validity of reductionistic statements. These statements are used in an attempt to describe the putative mechanisms of neurotransmitter action(s) to the fraction of the public that functions at no higher than a 6th grade reading level” (personal communication, 2002 April 11).The attempt to characterize demonstrably false claims as merely simplifications or partial explanations after appearing to acknowledge that they’re baseless is a fairly constant feature of the sorts of admissions I’m talking about here. No evidence for continued claims like “some abnormality in the serotonin system clearly plays a role” is provided or requested.
It is curious that these advertisements are rationalized as being appropriate for those with poor reading skills. If the issues surrounding antidepressants are too complex to explain accurately to the general public, one wonders why it is imperative that DTCA of antidepressants be permitted at all. However, contrary to what the FDA seems to be implying, truth and simplicity are not mutually exclusive. Consider the medical textbook, Essential Psychopharmacology, which states, “So far, there is no clear and convincing evidence that monoamine deficiency accounts for depression; that is, there is no ‘real’ monoamine deficit” [44]. Like the pharmaceutical company advertisements, this explanation is very easy to understand, yet it paints a very different picture about the serotonin hypothesis.
Further, the persistent acceptance of the existing model is portrayed as desirable and beneficial. People wanted it, and it’s been socially useful even if, as it unexpectedly turns out, much to their surprise, it's not backed by science. The articles often insist on including passages attributing the tenacity of the brain-disease-drug model to the demands of the psychologically distressed public. Hyman, for example: “Even if current drugs recycle old action in the brain, the existing pharmacopeia is a great blessing to many patients and their families.” Or Spiegel:
So why are so many people still talking about low serotonin causing depression?This is the standard narrative: the model is so popular because people want clarity and certainty, even if it’s false, and this model has provided them that. It’s also been beneficial because it’s reduced stigma. It’s not greed-driven corporations, a profession trying to gain status and money, or billions of dollars spent to market not just the drugs but the model itself that have been behind its cultural success – it was people’s need for simple solutions and the important destigmatizing function the model has served in the culture. (Really, we should all be thanking them!)
Frazer says it's probably because it has had, and continues to have, important cultural uses. For one, he says, by initially framing the problem as a deficiency — something that needed to be returned to normal — patients felt more comfortable taking a drug.
"If there was this biological reason for them being depressed, some deficiency that the drug was correcting," Frazer says, then taking a drug was OK. "They had a chemical imbalance and the drug was correcting that imbalance." In fact, he says, the story enables many people to come out of the closet about being depressed, which he views as a good thing.
But Delgado agrees with Frazer and says the story has some benefits. He points out that years of research have demonstrated that uncertainty itself can be harmful to people — which is why, he says, clear, simple explanations are so very important.
"When you feel that you understand it, a lot of the stress levels dramatically are reduced," he says. "So stress, hormones and a lot of biological factors change."
Like the model itself, these claims have an estranged relationship with the facts. The role of corporate marketing and psychiatric maneuvering (and media complicity) in pushing this model is extremely well documented, and the model is, in fact, stigmatizing. Even if this weren’t the case, as I’ve argued before, it’s not just condescending but fundamentally unprofessional and unethical for doctors, therapists, or government officials to lie to people because they think they want to be lied to or, worse, to get them to take drugs.
But these articles and reports aren’t particularly interested in evaluating the individual and social consequences of the model’s acceptance. Their purpose, it seems, is protecting the larger brain-disease enterprise. The framing of frank admissions that the model isn’t scientifically supported in the ways I’ve described sets the stage for the second part of the refrain: the breathless, almost comically arrogant predictions about the wondrous scifi possibilities of new research. The fact that the existing model is scientifically invalid can be pushed aside. New and exciting frontiers in genetics (of course) and imaging and so on are opening up that will save the day.
Hyman gushes:
As long as we guard against renewed self-deception about what constitutes meaningful advances, there is good reason to feel optimistic about the long-term future of translational psychiatry—despite its palpable scientific challenges. My optimism is based partly on the extraordinary vitality of neuroscience and perhaps, even more important, on the emergence of remarkable new tools and technologies to identify the genetic risk factors for psychiatric disorders, to investigate the circuitry of the human brain, and to replace current animal models that have failed to predict efficacious new drugs that act by novel mechanisms in the brain. New ideas are, of course, central to scientific progress, but new tools can open up unexpected worlds and thus undergird the formulation of truly novel hypotheses.David Adams writes,
…Our best hope is that the genetics will unfold over the next several years, due to the efforts of large international consortia that have formed to recruit and to study patients. As genetic clues accumulate, scientists are devising new ways to investigate their neurobiological functions and dysfunctions.
…The leading approach is to take a small skin biopsy from the arms of volunteers and to transform skin fibroblasts into neural progenitors and into neurons. Genetic engineering can then be used to add risk-causing mutations to “healthy” neurons and to reverse risk mutations in patients’ neurons. But it is still early in this new field, and it is not yet possible to engineer the specific kinds of neurons implicated in schizophrenia by postmortem studies.
This barrier is likely to fall soon. Whether or not engineered neurons or human neural circuits on a chip prove to be good systems for studying gene function, researchers will make substantial efforts to turn genetic clues into ideas for therapeutics. Many researchers hope that such efforts will help attract the pharmaceutical industry back to psychiatry by demonstrating new paths to treatment development. The emerging genetic results may be the best clues we have ever had to the etiology of psychiatric disorders. If other areas of medicine can guide us, there is enormous promise in deprioritizing existing drugs and old-fashioned animal-based assays as investigative tools and instead focusing on actual disease mechanisms identified by genetics. Technology has only recently begun to make this possible.
Research could yet come to the rescue. In 2010, the US National Institute of Mental Health (NIMH) in Bethesda, Maryland, launched an initiative, called the Research Domain Criteria project, that aims to improve understanding of dimensional variables and the brain circuits involved in mental disorders. Clinical psychologist Bruce Cuthbert, who heads the project, says that it is an attempt to go “back to the drawing board” on mental illness. In place of categories, he says, “we do have to start thinking instead about how these disorders are dysregulation in normal processes”.Here’s Insel’s description of the program:
…All involved agree on one thing. Their role model now is not Freud or Kraepelin, but the genetic revolution taking place in oncology. Here, researchers and physicians are starting to classify and treat cancers on the basis of a tumour's detailed genetic profile rather than the part of the body in which it grows. Those in the psychiatric field say that genetics and brain imaging could do the same for diagnoses in mental health. It will take time, however, and an entire generation will probably have to receive flawed diagnoses before the science is developed enough to consign the category approach to clinical history.
“I hope I'll be able to give a patient with possible bipolar a proper clinical assessment,” Craddock says. “I'll do a blood test and look for genetic risks and send them into a brain scanner and ask them to think of something mildly unhappy to exercise their emotional system.” The results could be used to trace the underlying cause — such as a problematic chemical signal in the brain. “I'll then be able to provide lifestyle advice and treatment.” He pauses. “Actually it won't be me, because I will have retired by then.”
NIMH has launched the Research Domain Criteria (RDoC) project to transform diagnosis by incorporating genetics, imaging, cognitive science, and other levels of information to lay the foundation for a new classification system. Through a series of workshops over the past 18 months, we have tried to define several major categories for a new nosology (see below). This approach began with several assumptions:Aside from drawing needed funds away from useful investigations into the social causes of psychological distress and the interventions it can lead to, and aside from its potential – given psychiatry’s history – of leading to dreadfully harmful “therapies,” this is simply a terrible approach to science. That should be obvious. You shouldn’t base your approach on a scientifically unfounded assumption, expecting that future discoveries will retroactively show that assumption to have been warranted.
• A diagnostic approach based on the biology as well as the symptoms must not be constrained by the current DSM categories,
• Mental disorders are biological disorders involving brain circuits that implicate specific domains of cognition, emotion, or behavior,
• Each level of analysis needs to be understood across a dimension of function,
• Mapping the cognitive, circuit, and genetic aspects of mental disorders will yield new and better targets for treatment.
…[P]atients and families should welcome this change as a first step towards "precision medicine,” the movement that has transformed cancer diagnosis and treatment. [my emphasis]
But of most interest here is the relationship of this futuristic speculation to the existing brain-disease-drug model. The aim appears to be the implicit suggestion that future discoveries will somehow, in some vague and unarticulated sense, rescue or validate it. Of course, that’s fundamentally not how science works – science is based on the evidence we actually have now, not on the expectation of some hypothetical evidence that could appear in the future. The evidence we have, as they acknowledge, is that the current biopsychiatric model is not supported by or consistent with scientific knowledge.
And they recognize that what they’re talking about is in essence a fresh, clean start. Adams writes that the new research program’s advances will “be too late for the DSM.” Spiegel, although he claims they’re making some (unspecified) progress, makes clear that “Researchers don't really know what causes depression.” Insel notes that “RDoC, for now, is a research framework, not a clinical tool. This is a decade-long project that is just beginning.” They talk about a new drawing board, scrapping the existing diagnostic categories, and “deprioritizing” existing drugs.
But at the same time they also seem to want to leave in place the current brain-disease framework, and to imply that research of the future will somehow vindicate it. But this is scientifically irrational. The odds, in particular, that genetics or imaging research over the next several decades will find something that supports the use of the current psychiatric drugs would have to be infinitesimal. And even if it were to happen, that wouldn’t justify their use now, with the evidence we have now. But these articles tend to obscure this. The second part of the refrain – the cheerful expectation for future research - serves rhetorically to minimize the very real, very serious problems with current practices that these articles are supposedly acknowledging.
The pharmaceutical companies have to walk a fine line. On the one hand, it’s about patents. They have to promote a model founding the efficacy and safety of their psychiatric drugs for as long as those continue to be patented and profitable; after they’ve exhausted all of their many means of extending the life of a patent for a drug, they have no reason to care. (Indeed, they’re happy to acknowledge the ineffectiveness of an off-patent drug if they’re trying to push a new one.) On the other hand, both they and the psychiatric-government-academic complex that has built up around these drugs need to sustain the model itself – both for the sales of other drugs (including any in the immediate pipeline) and for their future funding, sales, and status. These sorts of articles do that work.
Greg Benson at Mad in America criticizes some of Insel’s article, but also says: “That said, I appreciate what I think is commendable intellectual honesty on the part of Thomas Insel. Insel argues the historic failure of validity in trying to understand ‘mental disorders’ as medical conditions.” It would be more commendable, I think, if he didn’t repeatedly give these honest (if partial) admissions the same sort of spin. The spin isn’t going to stop on its own. The best that the supporters of science and social justice can do is to keep publicizing these admissions of the failure of the biopsychiatric model, becoming more aware of the techniques through which these are spun, and putting forward the real picture.**** I hope I’ve contributed a bit to that here.
* Note that I am not providing these quotations as primary evidence of the invalidity of the brain-disease model. That evidence is abundant, and I have linked to sources here many times.
** Well,…
*** Hyman’s article also points to the use of nonhuman animals in psychiatric research. The Catch-22 for advocates of this research is clear: if these animals are being used as models because they’re recognized (however dubious the specific assumptions being made) as sharing the capacity to become depressed, distressed, helpless, afraid, and so on, it’s hard for researchers to claim that the experiments aren’t cruel.
**** As Richard Bentall does here.
Saturday, May 4, 2013
Nonreligious God-given principles
Wayne LaPierre at the NRA meeting:
They want to change America. Change our culture. They want to change our values. But you know what? This is America – the first country in the world founded not on a race, not on a religion, not on a royalty, but on a set of God-given principles that we call inaliable [sic] rights.
God put him here to kill animals
These sorts of meetings seem to be a theme this week. Recently, I learned from the Animal Ag Alliance that God put other animals on earth to help and feed us. I’m now watching the surreal National Rifle Association annual meeting in Houston on C-SPAN. David Keene, who has all the charisma of a napkin dispenser, is praising the organization’s board of directors:
J.D. Williams of Oklahoma, Washington, DC, and now Texas is one such director. J. D. has been a mentor to Wayne [LaPierre], to me, and to the NRA itself for decades. As a successful attorney, and perhaps the most respected lobbyist of his generation, J.D. Williams has been instrumental in every single Second Amendment battle waged in Washington since the 1960s.What follows on C-SPAN? “MEDIA COVERAGE OF TRAYVON MARTIN CASE.”
He has been, and continues to be, a valued friend and advisor to Democrats and Republicans alike. He was crucial to the formation of the Institute for Legislative Action, and has been an unfailingly wise counselor to Wayne and to every NRA president with whom he has served. And would, if we were a baseball team rather than a board of directors, be a perennial Most Valuable Player.
I remember riding back to Washington with J.D. Williams many years ago after a day of waterfowl…shooting on the Chesapeake. He said he hadn’t hunted ducks and geese until well after he’d moved to Washington, but remembered coming back after his first hunt and saying to himself, “So, this, J.D., is why God put you on this earth.”
J.D. Williams is rarely wrong, but he was wrong that day. God put him on this earth to play a key role in the defense of freedom and the rights passed down to us by our founders. Although God really didn’t mind if he took a day off here and there to shoot a few guss and- …ducks and geese on the side.”
*According to his NRA biography, he’s dedicated to “hunters’ rights” and “personally financed the organization of the Congressional Sportsmen’s Caucus.”
Oppose Texas House Bill 2212
MindFreedom is calling on people to speak out against Texas House Bill 2212, which
will dramatically expand the population eligible for assisted outpatient commitment in this state. In a blatant assault on the right to bodily integrity, the bill would allow psychiatric interventions including what the state says is “clinically necessary medication” to be administered by force to law-abiding citizens living in the their own homes based on a few, elastic criteria.As they note, their opposition to such policies is shared by the UN Special Rapporteur on Torture and Human Rights Committee and supported by the scientific evidence, including this recent article in the Lancet. (Tom Burns, the lead author and a former advocate of Community Treatment Orders, is now calling for a moratorium. My favorite quote is from the comments: “'Tabloid-inspired legislation turns out to be ineffective' shocker.”)
The bill has been pending in committee since March 27. I’m not sure what if anything that means.
Friday, May 3, 2013
Unconscionable by any measure
One remark in Matthew Spiegl’s piece about the recent SeaWorld IPO stood out:
“[T]o perpetuate the practice of keeping orcas in captivity is unconscionable by any measure of any standard in today's society.”
Not much more to say.
In searching for more about the IPO, I came across references to a new documentary, Blackfish.
Here are a review of the film and an interview with the director, Gabriela Cowperthwaite.
In related news, the Free Morgan Foundation linked to a legal analysis of the Morgan case in the journal Transnational Environmental Law, which the journal has made available for free.
Thursday, May 2, 2013
The theology of animal ag
Will Potter posted* about the exclusion of critical journalists and lawyers (I wonder if there were any critical academics…) from the Animal Agriculture Alliance-hosted “Activists at the Door” conference which just concluded. It was later learned that sessions can be watched online (link at his post), but I’m also enjoying the AAA twitter feed.
There are tweets and retweets about transparency:
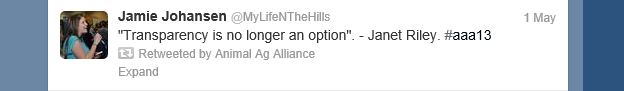
Heh.
There’s a tweet about the importance of chefs in shaping the culture of the way we eat.

There’s one about parody videos and…“agvocating.”

Because there’s nothing more hilarious than corporate-produced parodies, especially of people and organizations exposing cruelty to animals.
Most interesting were a couple of retweets about their “industry” and divine will:


Of course.
*See also here!
S.H.A.M.E. Project's latest profile
There was Charles Murray, brave hero dedicated to advancing pure, dispassionate, wholesome science, and along came those femistasi, afrostasi, and pooristasi with their evidencist political agendas.
Why do they continue to do this?
Another article I came across in the past few days concerned PETA’s attempts to get Washington University in St. Louis to stop using cats in its Pediatric Advanced Life Support (PALS) intubation training. Apparently, they’ve been calling for an end to the practice there for a few years already, and recently Bob Barker offered to give the university $75,000 for the purchase of simulation mannequins.
WUSTL doesn’t seem to want to take Barker’s offer and switch to the use of mannequins, and I can’t understand why. Other training facilities use the mannequins (I haven’t been able to determine whether most or all others do), and the American Heart Association responded to a question from PETA by saying: “We do not endorse or require the use of animals during the AHA-PALS training because of advances and availability of simulation mannequins.”
This would seem to settle it. Other programs use mannequins, the AHA supports the use of mannequins, someone’s offering to pay for the mannequins – why would they continue to use cats? I don’t get it. Is there something I’m missing here?
saddened
In the video I linked to in my previous post, people mentioned the cat issue. They were referring to recent conflict surrounding research on cats like the one shown here in photos PETA obtained from the University of Wisconsin-Madison through FOIA.

I saw it the other day, looked at the orange tabby sleeping contentedly by me on his bed, and I was shaken. I’m not interested in debating PETA’s tactics or the accuracy of their communications (including this one), the use of “emotive” images in moral debates, the progress of medicine, or anything else here. I just wanted to share the pictures and my reaction. I’m still shaken, and saddened.
Wednesday, May 1, 2013
What kind of bogus requirement is that?
Here’s a (relatively) recent talk and discussion with philosopher Lori Gruen about research on nonhuman animals:
Prof. Lori Gruen "Animal Research and the Limits of Medicine" from luciano M on Vimeo.
I found it through this post by Dario Ringach, whose response was at times odd:Prof. Gruen offered a couple of examples of research we would all consider to be off limits, however she struggled to apply her own criteria to give us instances of invasive, biomedical experiments she feels are morally justified. When challenged to list a such examples, she paused for a while, and then offered a rather unsatisfactory response — “This is too big a question.”This is strange and in some ways bizarre. First, that wasn’t the entirety of her response, as Ringach must know. Second, the last two questions rest on a misunderstanding which he seems to promote consistently: that the nonspeciesist and moral individualist contention is that scientists should perform the experiments they perform on animals on cognitively impaired children instead (or additionally). That is not an argument I’ve ever heard them make, and it wouldn’t make sense for them to do so. They object to the suffering caused to beings with certain relevant capacities regardless of species. It would be utterly bizarre for them to endorse such experiments on humans. They’re saying, “We draw lines around what we can do to humans experimentally, and the same considerations behind prohibitions on human research should apply to any beings with the same relevant characteristics and capacities. Drawing the line around our species isn’t scientific or consistent with the ethical principle underlying the human prohibitions; it merely reflects human prejudice. This means that research we wouldn’t perform on impaired (and abandoned) human children shouldn’t be performed on any animals with comparable characteristics.”
Unfortunately, making such moral judgements is at the heart of the issue....
If moral philosophers want to have an active participation in the ethical decision process they must be able to answer how and when they will find a particular research proposal justified or not. The public (which is certainly a stakeholder in the research as much as those that would like to advocate for much stricter limits [I’m confused as to why he doesn’t regard these people as part of the public. – SC]) would very likely want to know, for example, if Prof. Gruen would have approved of the use of animals in the development of the Polio vaccine, or the use of mice to develop new therapies for aggressive forms of breast cancer, or the use of rats to develop a cure for paralysis? Would she have approved these projects only if the investigators expressed their willingness to experiment on cognitively impaired children as well? If so, would she endorse such experiments herself?
But it’s the assumption underlying the challenge to Gruen that stood out to me. Ringach seems to be arguing that ethicists only have a valid place in the discussion if they can point to invasive biomedical experiments on animals that they believe are or were justified. Indeed, he wants to make this a requirement for participation: “If moral philosophers want to have an active participation in the ethical decision process they must be able to answer how and when they will find a particular research proposal justified or not.” Since he’s acknowledged that she offered several examples of research that she believes is or was unjustified and why, he’s clearly suggesting that she and other ethicists must either stipulate that some real cases of invasive biomedical research on animals have been justified or stand down.
But this is a bogus requirement. It’s entirely possible for an ethicist, even one who hasn’t set forth absolute limits, to find that in light of their ethical framework no past or existing examples of research have been justified. It’s also possible for someone to conclude that, since the cases that might conceivably be justified are extremely rare and that in a system that broadly accepts this sort of research the incentives to expand the range of so-called justified cases are strong, it’s best to set general limits, be they that some species can’t be experimented on, some procedures can’t be done, some fields of research animals can’t be used in, or that invasive biomedical research on animals be prohibited or allowed only in the rarest of cases (which might in practice remain entirely hypothetical). (I’m not saying either of these characterizes Gruen’s position – I’m addressing Ringach’s suggestion.)
This is the case with human research subjects, after all. The Declaration of Helsinki sets strict limits on the invasive biomedical procedures that can be done on humans. And this is precisely because of a long history, culminating in Nazi human experimentation, of using some groups of humans instrumentally to benefit (allegedly) other humans. Sadly but predictably in the current system, these standards are constantly chipped away at in order to use less powerful humans as research subjects, be they people with a psychiatric diagnosis; poor people in India, Nigeria, Russia, Honduras; children;... And the rules are often flouted in practice, for a variety of motives.
But they’ve held as moral lines, and become embedded in laws and institutions worldwide. And you don’t typically hear suggestions that people be excluded from the conversation about human-subjects ethics because they reject, say, all nonconsensual research on human beings. You don’t see people’s participation premised on their acknowledgment that research on slaves or children in orphanages produced valuable medical knowledge that benefited people and was therefore “justified.”
The development of this consciousness and its institutionalization reflects real changes in our societies and how we value human beings. Ethical lines that used to be drawn around races or nationalities or other categories are recognized as reflecting prejudices,* and what were previously accepted as high-minded justifications based on scientific progress or human betterment have been revealed as self-serving rationalizations, or at the least as failing to rise to the challenge of justifying nonconsensual invasive biomedical research in humans. Even if the research had a high likelihood of contributing to human well-being – and a very large portion of it does not, and is sometimes actively harmful - that doesn’t justify the harm caused to the real humans who are used as research subjects or to ourselves as a society that condones their exploitation.
So it’s remarkable that in the comments Ringach appears to be arguing that ethicists actually have no substantial critical role to play, and in fact fundamental case-by-case assessment of justification isn’t necessary, because all that needs to happen is that a society democratically accept that invasive biomedical research on nonhuman animals alleged to advance of human wellbeing is basically justified, and this is something our society has already done:
I do not deny there is a role for stakeholders to participate in research after we agree this is something we, as a society, find morally justifiable to do. That’s the larger question that needs to be answered. If society says “no”, then scientists would have no option but to accept their decision. If society approves, one can only hope the opposing side will accept the decision as well. Unfortunately, dialogue at times seems futile because there is a growing segment of the animal rights movement that is not looking to resolve a moral dispute democratically. Some of them feel entitled to use violence to impose their views on the rest of society.(This puts his discussion of individual cases in a new light: the point, it seems, of requiring that animal advocates “acknowledge” that research is or might be justified in some cases is really understood as getting them to consent to some sort of basic intrinsic acceptability of animal research – to saying “yes.”) Setting aside that he does here again what I challenged above – assumes as a requirement the very thing that’s at issue in these ethical debates: that the only acceptable position is that “this is something...morally justifiable to do” – this looks suspiciously like an attempt to remove the issue from the realm of public ethics entirely. On what does “society” base its decisions? Ideally, on relevant evidence and moral arguments. What Gruen is saying, correctly in my view, is that this is a moral discussion our society hasn’t really even begun to have in earnest, much less resolved, and that we need to have it in earnest.
This needed public discussion very naturally involves ethicists and animal advocates, including those who oppose most or all invasive biomedical research on animals. And scientists are not nonpeople standing outside of this process, uninfluenced by the prevailing ideology and carrying no moral responsibility for their actions. They’re people who inevitably bear the weight of their actions – including the violence they inflict on nonhuman animals (culturally condoned and legally permitted violence is still violence, as is violence committed in the name of a greater good**) – and need to participate in the public discussion and address the arguments of those who oppose some of their actions.***
As the information found through my links above shows, it’s incredibly naive to propose that the situation in the US as it currently stands in this case or any other is the result of a democratic societal deliberation and decision. Such questions are “settled” in a context of economically and politically powerful corporations and governments – wielding an enormous capacity to propagandize in favor of their interests, conceal their actions, mislead the public, and impose their vision and practices on human and nonhuman animals. Practices continue from inertia, intellectual laziness, and the fear of deeply questioning the morality of our own past or current actions. Those harmed often have little political power or economic resources, and they and their advocates are excluded, often forcibly, from the decision-making.
But movements persist, and the exploitation of animals is increasingly recognized as a social issue in need of robust public discussion. When we look at the changes in actions toward other humans in our society, we see a tragic history of people and organizations deciding, democratically and otherwise, that nonconsensual invasive biomedical research on “lesser” humans was “something morally justifiable to do.” We see other people challenging them in words and other actions, and we can trace a transformation in public attitudes and a corresponding transformation of law and institutional practices in the direction of recognizing human rights in research and limiting what can be done to people. A parallel transformation has been occurring globally with regard to experimentation on nonhuman animals. Although the US is, typically, a laggard, even our country has been moving in this direction, as indicated by the recent IOM report and subsequent NIH decisions about chimpanzee research.
*And it shouldn’t be forgotten that the lines within our species are not disconnected from the line between human and nonhuman animals. The acceptance of research on nonhuman animals always leaves open the door for accepting nonconsensual research on “lesser” humans. Always.
**I’ll take this opportunity to recommend again De Beauvoir’s The Ethics of Ambiguity.
***And scientists don’t in any meaningful way “speak for science.” They’re as capable as anyone else of coming to their own conclusions and changing their minds and practices.
Subscribe to:
Posts (Atom)
